

Facial skin cancer
Oncological rigour combined with aesthetic precision.
Duration
30 minutes to 2 hours
Anaesthesia
Local, conscious sedation or general depending on the extent
Hospital stay
Usually a day case
Recovery
Histology results within 7 to 10 working days
Where the health of your skin meets the art of facial reconstruction. A suspicious skin lesion on the face, eyelids, nose, lips or neck immediately raises two crucial questions: will the tumour be removed completely and for good? And will my face keep its harmony, its expression and its natural look?
As a surgeon specialised in the head, face and neck, Dr Yousefpour provides a comprehensive answer to both. With in-depth command of head and neck anatomy, every operation is conceived from the outset as a dual act: eradicating the disease to the strictest oncological standards and reconstructing the tissues according to the golden rules of plastic and aesthetic surgery.
The protocol, step by step.
- Step 1
Consultation and clinical mapping
Dermoscopic analysis, 3D anatomical assessment of the lesion, diagnostic biopsy if needed and an in-depth discussion of the reconstruction strategy.
- Step 2
Tailored surgery
Performed under local anaesthesia, conscious sedation or general anaesthesia, depending on the extent of the excision and whether neck surgery is needed.
- Step 3
Pathology confirmation
Systematic histological examination of the specimen to confirm the diagnosis and the complete absence of residual tumour at the margins (clear R0 margins).
- Step 4
Post-operative scar care
Massage protocols, silicone dressings, sun protection and rigorous periodic oncological surveillance.
Our areas of treatment and conditions managed
Early diagnosis and careful analysis of the skin architecture are essential:
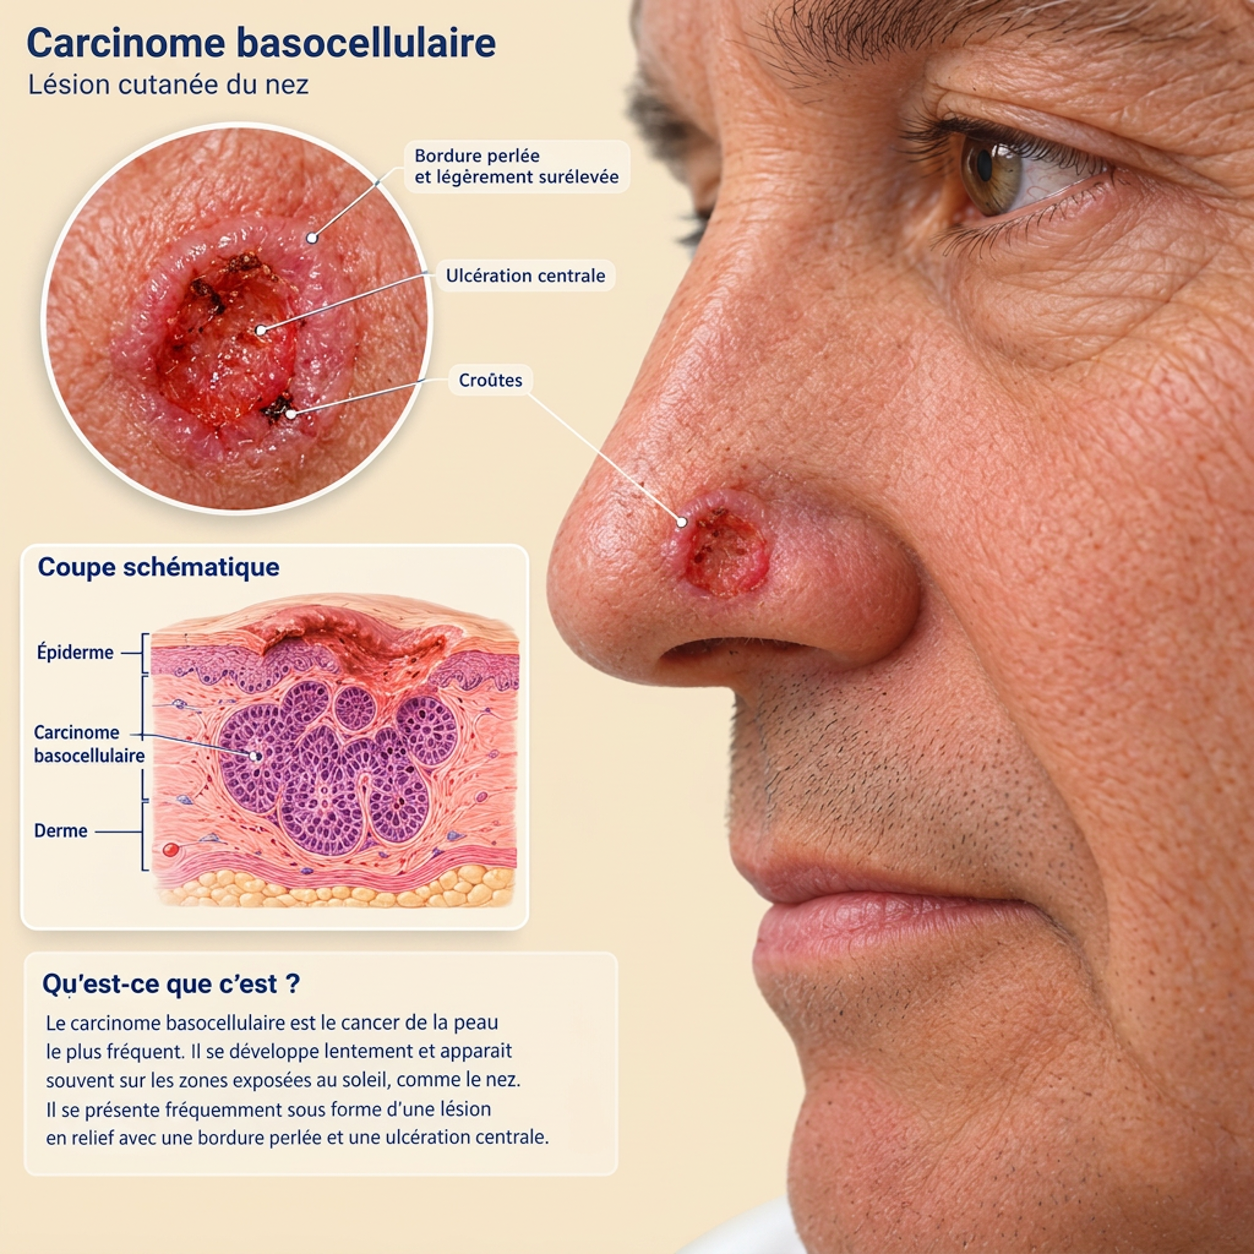
Basal cell carcinoma (BCC): the most common skin cancer, often caused by repeated sun exposure. Although it grows slowly and does not usually spread to the lymph nodes, its local growth on the face (nose, ears, temples) requires millimetre-precise excision to preserve key structures.
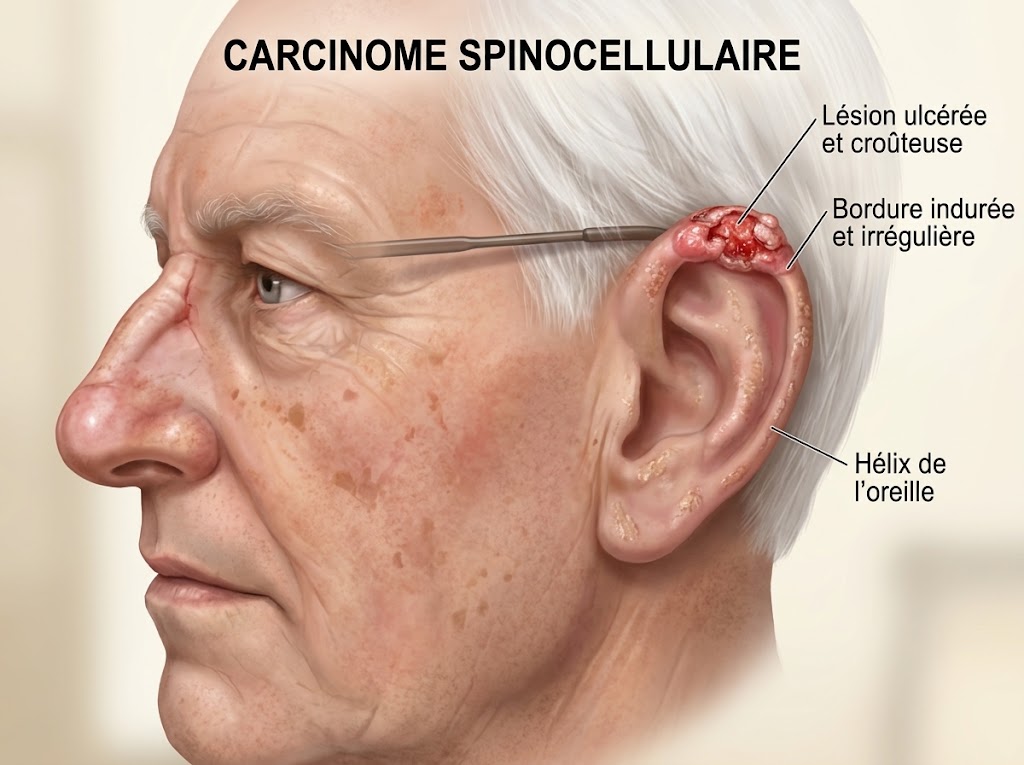
Squamous cell carcinoma (SCC): a more aggressive tumour that can invade the underlying tissues and spread to the lymph nodes of the neck. It requires a rigorous excision strategy and careful lymph node surveillance.
Cutaneous melanoma of the head and neck: highly specialised surgical management with three-dimensional margins adapted to the Breslow thickness, and precise assessment of the lymph node chains of the neck.
Pre-cancerous lesions and rare tumours: severe actinic keratoses, Bowen’s disease, Merkel cell carcinomas and dermatofibrosarcomas.
Oncological excision with controlled margins
Cure is the absolute priority. Dr Yousefpour applies the strictest international protocols to remove the lesion with clear safety margins (at the surface and in depth), ensuring maximal local control.
Immediate aesthetic reconstruction: preserving your identity
Removing a tumour should not disfigure. Thanks to his command of facial plastic surgery, Dr Yousefpour mobilises neighbouring tissue along precise anatomical planes:
Local advancement, rotation and transposition flaps: tailored redeployment of adjacent skin with the same texture, colour and thickness.
Respect for the aesthetic units and subunits of the face: incisions are hidden in natural grooves, expression lines (Langer’s lines), the eyelid contour, the nostrils or the hairline.
Composite or full-thickness skin grafts: taken from discreet sites (behind the ear, above the collarbone) when tissue preservation requires it.
Neck management and lymph node dissection
Unlike purely dermatological or superficial cosmetic treatment, Dr Yousefpour’s head and neck surgical training allows him to manage the whole extent of the tumour, including when it reaches the lymph nodes of the neck:
Selective or modified radical neck dissection: removal of all lymph nodes that are involved or at high risk of metastasis.
Functional preservation of nerves and vessels: millimetre-precise dissection protecting the facial nerve (marginal branch), the spinal accessory nerve (shoulder movement), the vagus nerve, the carotid artery and the internal jugular vein.
Frequently asked questions
Will I have a visible scar on my face? Every skin incision leaves a mark, but the visibility of the scar depends entirely on the closure technique. Incisions are hidden in the shadows and natural creases of the face (nasolabial folds, forehead lines, crow’s feet, grooves behind the ear); tension is taken up in the deep layers with invisible dissolvable sutures, allowing a fine, flat and discreet scar.
What difference does a head and neck surgeon’s expertise make? The head and neck concentrate a unique density of anatomy: motor nerves of facial expression, cartilage of the nose and ears, salivary ducts and major blood vessels. A surgeon specialised in this region can excise the tumour without damaging these structures, reconstruct the facial contour and treat the neck nodes if the tumour has spread.
Why and when is a neck dissection performed? Some aggressive skin cancers (melanomas, extensive squamous cell carcinomas) tend to spread to the neck nodes. When these nodes are suspicious or confirmed to be involved, neck dissection is the only curative and definitive surgical treatment; it eradicates regional disease before it spreads to the rest of the body.
What anaesthesia is recommended? Excision of a standard lesion with immediate local-flap reconstruction is usually done under local anaesthesia alone or with intravenous sedation, as a day case. When a complex reconstruction with a large flap or a neck dissection is needed, the operation is performed under general anaesthesia.
How long do histology results take? The specimen is sent to the laboratory the same day. Full results (nature of the lesion and status of the margins) are usually available within 7 to 10 working days, at the post-operative check-up.
Medical information: nature of the operation
Dr Yousefpour explains the indications, the oncological goals and the personalised reconstruction plan. Depending on your situation, the operation includes:
Complete oncological excision of the skin lesion with an appropriate safety margin.
Systematic pathological analysis in a specialised laboratory.
Aesthetic and functional reconstruction (direct closure, local advancement or rotation flap, skin graft).
If indicated: neck dissection as definitive surgical treatment in case of spread or regional lymph node risk.
Potential risks and complications
Although performed with great technical care in a sterile, compliant surgical setting, every operation carries risks:
General and scar complications: bleeding, haematoma that may need draining, temporary facial bruising; wound infection requiring local care or antibiotics; delayed healing, partial necrosis of the skin edge or flap (particularly in smokers); unsightly, hypertrophic or discoloured scars that may need prolonged care or revision.
Reconstruction and nerve complications: temporary reduced or lost sensation around the operated area; temporary asymmetry or slight tightness when moving the face during healing.
With a neck dissection: temporary (very rarely permanent) weakness or paralysis of the marginal branch of the facial nerve (asymmetric smile) or of the spinal accessory nerve (difficulty raising the shoulder); lymph collection (lymphocele) or neck swelling that settles over time.
Oncological risk: a further operation (re-excision of the margins) may be needed if pathology shows microscopically insufficient margins.
Recommendations and patient commitment
To optimise the oncological and aesthetic result, you undertake to:
Report any anticoagulant or antiplatelet treatment and any drug allergy.
Stop smoking completely for at least 2 to 4 weeks before and after the operation to avoid skin necrosis.
Avoid direct sun exposure on the scars for at least 12 months (sunscreen SPF 50+).
Attend the scheduled post-operative check-ups and oncological surveillance appointments.
Informed consent
You receive a medical information and informed consent document before the operation. By signing it, you confirm that you have read and understood this information, received clear explanations of the condition, the treatment options, the cancer surgery, the reconstruction and, where applicable, the neck dissection, been able to ask all your questions, and give your free and informed consent.